This albumin correction factor for anion gap acts as a way to correct the anion gap when albumin is decreased. Because albumin is a primary unmeasured anion in the blood, hypoalbuminemia can make the gap look lower than it actually is. A reliable Anion Gap Calculator can apply this adjustment so the result better reflects the patient’s true acid-base disorders status.
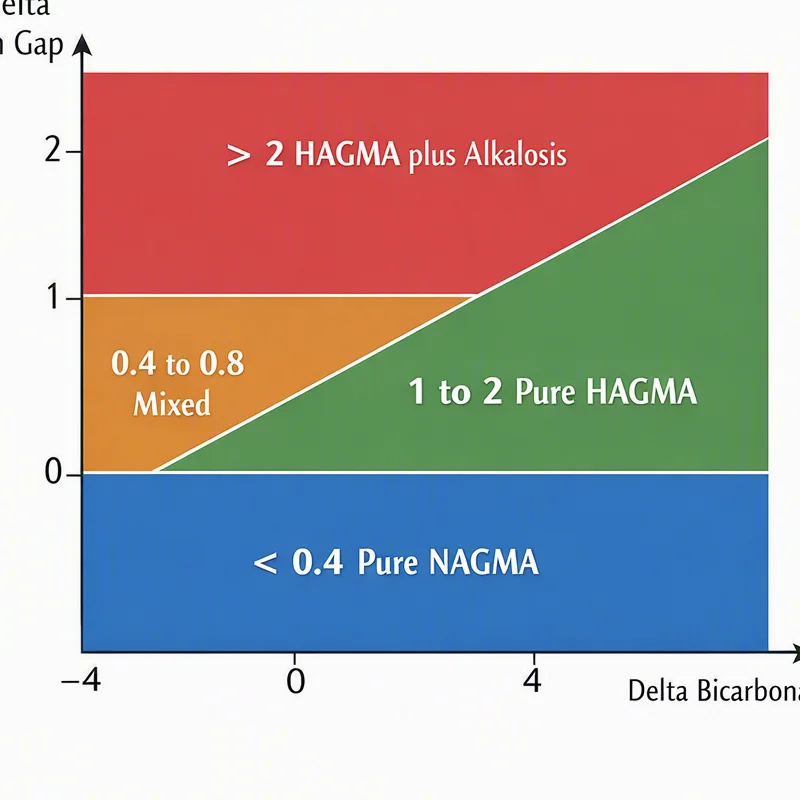
The most widely used correction is 2.5 mEq/L per 1 g/dL albumin under the usual serum albumin reference range. Put simply, if albumin is low, the corrected anion gap rises to compensate for the missing negative charge from albumin and enhance laboratory interpretation.
What Is the Anion Gap?
The anion gap is a calculated value that helps clinicians interpret serum electrolytes and screen for acid-base disorders. It is typically based on serum sodium, serum chloride, and serum bicarbonate. The classic formula is:
Anion gap = sodium − (chloride + bicarbonate)
This value reflects the gap between routinely measured positively charged ions and negatively charged ions in the blood. In blood chemistry, a normal gap implies balanced unmeasured ions, while an abnormal gap can indicate a metabolic derangement. The anion gap is most often used in acid-base evaluation to help identify metabolic acidosis, especially when the cause is not obvious from the initial lab results.
Understanding the gap requires more than memorizing a formula. It also helps to know that the gap is influenced by unmeasured ions, especially protein anions such as albumin. That is why the measured value can change even when the clinical situation has not changed for the better or worsened.
How Albumin Affects the Anion Gap
Albumin is the key negatively charged protein in plasma. Since it adds many protein anions, it has a strong effect on electrolyte balance and the measured anion gap. When albumin falls, the body loses some of those undetected negative charges, so the anion gap may decline as well.
This explains why hypoalbuminemia can mask an underlying acid-base problem. A patient may present with a normal gap even when there is actually a high-gap disorder present. That can lead to missed hidden acidosis unless the albumin level is evaluated.
Albumin matters because acid-base chemistry is about charge balance. If fewer albumin molecules are present, fewer negative charges are available. The result is a reduced measured gap, even though the true acid-base balance may be abnormal. This is one of the most important reasons to incorporate albumin into diagnostic interpretation.
What’s the Albumin Correction Factor?
The albumin correction factor is the quantity added to the measured anion gap to account for low serum albumin level. The common correction equation uses 2.5 mEq/L for every 1 g/dL decrease in serum albumin below the standard reference level, often taken as 4.0 g/dL.
In practice, the formula is often written as:
Corrected anion gap = measured anion gap + 2.5 × (4.0 − serum albumin)
This adjustment approximates what the anion gap in chronic kidney disease gap would look like if albumin had been normal. It turns a observed value into a more clinically meaningful corrected value. For many clinicians, this improves clinical utility when evaluating acid-base imbalance and deciding whether further workup is needed.
The key point is that the correction is an approximation, not a perfect truth. Still, it is widely used because it improves lab result interpretation, especially when the albumin level is clearly below the usual reference range.
How to Correct the Anion Gap for Albumin
Correcting the anion gap is simple once you know the measured anion gap and the serum albumin level. The process is simple to apply in a calculator or by hand.
How to calculate:
- Find the measured anion gap from sodium, chloride, and bicarbonate. Verify the serum albumin value and ensure the units are in g/dL. Deduct the albumin from 4.0 g/dL, if 4.0 is the reference point being used. Calculate that difference by 2.5 mEq/L per 1 g/dL albumin. Include the result to the measured anion gap.
Worked example:
If the measured anion gap is 10 mmol/L and serum albumin is 2.0 g/dL:
Correction = 2.5 × (4.0 − 2.0) = 5.0 mEq/L
Corrected anion gap = 10 + 5 = 15 mmol/L
This illustrates why consistent units matters. Although the correction is often written as mEq/L, the anion gap is commonly reported in mmol/L, and many labs use the terms interchangeably in this context. The essential step is to keep units consistent and understand how the calculator handles them.
A useful Anion Gap Calculator automates this process and reduces calculation errors. It can also support more efficient medical calculator use at the point of care, where quick clinical interpretation is often needed.
When to Use an Anion Gap Calculator
An Anion Gap Calculator is particularly useful when you are checking lab values in a patient with low albumin or unclear acid-base findings. It connects routine chemistry results with a more precise acid-base picture.
Use a calculator when:
- Albumin is below normal and you want an albumin-adjusted anion gap. You suspect metabolic acidosis but the gap appears normal. The clinical picture suggests acid-base evaluation is incomplete without correction. You want a quick diagnostic interpretation at the bedside or during chart review.
The calculator is especially valuable in hospitalized patients, critically ill patients, and anyone with changing protein levels. In these settings, the measured value may not reflect the true corrected value. By adjusting for albumin, the calculator improves clinical utility and can uncover a metabolic problem that would otherwise be overlooked.
Frequent Causes of a High or Anion Gap
When reviewing metabolic acidosis, the anion gap helps separate between high anion gap metabolic acidosis and normal anion gap metabolic acidosis. A adjusted result can change your reading from one group to another.
Typical causes of high anion gap metabolic acidosis include:
- Acidosis from lactate buildup Ketoacidosis Renal failure Other types of acid buildup or toxic exposure
In lactic acidosis, elevated lactate adds unmeasured anions to the blood. In ketoacidosis, ketone bodies elevate the gap. In renal failure, stored acids collect and raise the anion gap.
A normal measured gap does not always exclude a high-gap process if albumin is low. That is where the albumin correction factor becomes important in practice. By correcting for hypoalbuminemia, you may reveal a true high-gap state that was hidden by a apparently normal result.
Common Errors in Albumin Correction
Several mistakes can reduce the usefulness of albumin correction in daily clinical interpretation. Most of these are straightforward, Go to this site but they can lead to significant analysis errors.
Typical errors include:
- Using the wrong values for albumin or the anion gap Selecting the wrong normal range for serum albumin Forgetting that the correction is only an estimate Ignoring other electrolyte abnormalities Interpreting the corrected anion gap without considering the full clinical picture
Another common issue is overlooking related chemistry results such as free calcium. Although ionized calcium is not part of the formula, it can be important in the broader evaluation of acid-base and electrolyte disorders. The same is true for other markers that affect interpretation of the patient’s condition.
Keep in mind that a corrected anion gap should not replace clinical judgment. It is a tool that improves diagnostic interpretation, not a standalone diagnosis. Carefully consider the full pattern of blood electrolytes, symptoms, and context.
FAQ On Albumin Correction and Anion Gap
Does low albumin always mean the anion gap is falsely low?
No. Reduced albumin often lowers the anion gap, but not every low value is misleading. The effect depends on the degree of albumin reduction, the overall gap interpretation, and the rest of the lab pattern. Low albumin can create apparently normal results or make a truly abnormal gap appear less impressive, which is why correction is helpful.
What correction factor is most commonly used?
The most common correction uses 2.5 mEq/L for every 1 g/dL drop in blood albumin below about 4.0 g/dL. This produces an albumin-adjusted anion gap that better reflects the patient’s acid-base status.
Can the corrected anion gap change diagnosis?
Yes. In some patients, correction can reveal metabolic acidosis that was hidden by low albumin. This may expose occult acidosis and affect clinical decision-making, especially when deciding whether to investigate causes such as lactic acidosis, ketoacidosis, or renal failure.
What is the albumin correction factor for anion gap?
This albumin adjustment factor is usually 2.5 mEq/L per 1 g/dL albumin below the normal reference point. It is added to the measured anion gap to determine a better corrected anion gap when albumin is low.
Why does low albumin decrease the anion gap?
This protein bears negative charge as a leading protein anion components in plasma. With lower albumin levels, the blood has less unmeasured negative ions, so the anion gap reading falls. This can alter acid-base evaluation unless correction is made.
How do you determine the adjusted anion gap?
Use the measured anion gap and include 2.5 times the difference between 4.0 g/dL and the actual serum albumin. A straightforward formula is: corrected anion gap = measured anion gap + 2.5 × (4.0 − serum albumin). This serves as a helpful calculation example for any medical calculator or manual assessment.
What’s the most common correction used for albumin?
The most frequently used correction is the 2.5 mEq/L per 1 g/dL albumin adjustment. It is widely used because it gives a useful estimate for the albumin-adjusted anion gap and enhances diagnostic interpretation in patients with decreased albumin levels.
At what point should a corrected anion gap be interpreted clinically?
Interpret the corrected anion gap when low albumin levels could be masking an acid-base problem, especially in suspected metabolic acidosis. It is most clinically useful when reviewing lab result interpretation in patients with unexplained illness, critical disease, or possible hidden acid accumulation.