What Is a Mixed Acid-Base Disturbance?
A combined acid–base imbalance occurs when several factor is altering acid-base balance at the same time. Instead of having a one simple pattern, the blood demonstrates evidence of several simultaneous abnormalities. That is crucial because a patient may seem acidotic, alkalotic, or even close to normal on paper while still having a serious root problem.
The typical combinations involve metabolic acidosis along with a different condition such as respiratory alkalosis. Clinically, this means one condition is lowering bicarbonate or adding to acid load, while another is reducing carbon dioxide through overbreathing. The effect can be puzzling unless you use a thorough clinical approach and interpret the full clinical picture.
A combined acid–base disorder is not just a laboratory curiosity. It often reflects a major metabolic disturbance, respiratory compensation that is excessive or insufficient, or an separate problem affecting the lungs and kidneys at the same time. Because of that, laboratory interpretation should always include serum chemistry, blood gas analysis, and the clinical context.
What Is Elevated Anion Gap Indicate?
The anion gap is a computed value used to detect changes in electrolytes and acid-base status. It estimates the difference between measured cations and measured anions in the serum, and it offers a clue about the presence of unmeasured anions in the bloodstream. When the elevated anion gap is present, it usually suggests that extra acids are accumulating.
An increased anion gap is most closely associated with high anion gap metabolic acidosis. In this pattern, bicarbonate is depleted while acids build up, leaving behind negatively charged byproducts that are not directly measured on a standard panel. These may come from lactic acid, ketones, toxins, or impaired renal function.
Understanding the anion gap helps narrow the differential diagnosis. It does not tell you the exact cause by itself, but it strongly suggests that the body is dealing with a specific type of acid loading or loss of acid excretion. That is why the anion gap is such a helpful part of laboratory interpretation.
How the Anion Gap Calculator Helps Interpretation
An Anion Gap Calculator streamlines the anion gap formula easier to apply and helps reduce mistakes during fast assessment. The calculation typically uses serum sodium, serum chloride, and serum bicarbonate. Because these values are often already available on a standard metabolic panel, the calculator turns raw serum chemistry into a more clinically meaningful result.
The classic formula is: sodium minus the sum of chloride and bicarbonate. That calculated value is the anion gap. A higher number suggests the presence of extra unmeasured anions and may indicate a high anion gap metabolic acidosis. The calculator can also help you spot whether the pattern matches a single disorder or points to a mixed acid-base disorder.
Using an Anion Gap Calculator is valuable because the result alone is not enough. You still need to compare it with the blood gas, the pH, the pCO2, and the patient’s symptoms. In other words, the calculator aids clinical reasoning, but it does not replace it. The best use is as part of a broader diagnostic approach that includes compensation analysis and an underlying cause review.
Typical Causes of Mixed Acid-Base Imbalances With High Anion Gap
A number of conditions can lead to a mixed acid-base imbalance with an high anion gap. The most common are lactic acidosis, ketoacidosis, and renal failure. Each can produce a high anion gap metabolic acidosis, and every one can also occur along with another process such as respiratory alkalosis or strong respiratory compensation that is greater than expected.
Lactic acidosis occurs when tissues are deprived of adequate oxygen or when cells cannot process oxygen normally. The consequence is increased lactate production and acid buildup. It is often seen in critical illness, inadequate blood flow, seizures, or substantial metabolic stress. If the patient is also hyperventilating, a respiratory alkalemia may occur simultaneously and make the pH less clearly abnormal.
Ketoacidosis happens when ketone production rises, most often in poorly controlled diabetes, prolonged fasting, or alcohol-related metabolic stress. The ketoacids increase the anion gap and decrease bicarbonate. If the person is breathing rapidly from pain, anxiety, infection, or sepsis, the blood gas may show a second disorder on top of the acidosis.
Renal failure can also result in retention of acids that are normally removed by the kidneys. As kidney function worsens, unmeasured acids accumulate and the serum anion gap may go up. This can happen gradually or rapidly, and it often requires thorough review to patterns of electrolyte disturbance and the full serum chemistry profile.
Recognizing a Mixed Disorder in Lab Results
The main step in recognizing a mixed acid-base disorder is not just observing an abnormal number. You need to read the arterial blood gas, including pH and pCO2, together with the chemistry panel. The combination tells you whether the body’s response is appropriate or whether two separate processes are happening together.
A blood gas may show a low pH with low bicarbonate, which fits metabolic acidosis. But if the pCO2 is lower than expected, there may also be respiratory alkalosis. That is why the idea of a mixed disorder becomes important. The pH alone may not reveal the full story, especially if compensation is masking one component.
The delta gap is a second useful tool. It compares the rise in anion gap with the fall in bicarbonate. If the changes do not match expected patterns, a mixed process may be present. For example, a very high anion gap with only mild bicarbonate reduction may suggest an additional metabolic alkalosis. Likewise, an unexpectedly low pCO2 may point to superimposed respiratory alkalosis rather than simple compensation.
In everyday interpretation, abnormal labs should raise questions like: Is the pH acidemic or alkalemic? Is the pCO2 moving in the direction you would expect? Does the anion gap fit the degree of bicarbonate loss? These questions help distinguish a straightforward pattern from a more complex metabolic disturbance.
Step-by-Step Approach to Understanding Results
A clear process makes analysis much easier. Initially, review the pH to determine whether the patient is too acidic, too alkaline, or approximately normal. Afterward, establish whether the primary process looks metabolic or respiratory. Then, review the serum anion gap to see whether there is evidence of increased anion gap metabolic acidosis. This order offers a useful foundation for laboratory interpretation.
Next, use Winter's formula to estimate the expected respiratory compensation for metabolic acidosis. If the measured pCO2 is much higher than expected, there may be an additional respiratory acidosis. If the pCO2 is well below than expected, respiratory alkalosis may be present. This is one of the key steps in identifying a mixed acid-base disorder.
Lastly, assess whether the observed pattern fits the expected physiology. True compensation is the body’s normal response to a primary disorder, but compensation has constraints. When the blood gas does not align with the expected pattern, it suggests more than one process. That is often the hint that the patient has an underlying cause requiring immediate attention.
A simple rule: if the anion gap is elevated and the pCO2 does not match the expected compensatory response, think beyond a single diagnosis and look for a second acid-base process.
Illustrations of Elevated Anion Gap Mixed Disorders
A typical example is a patient with sepsis who develops lactic acidosis. This infection drives poor tissue perfusion and lactate buildup, causing marked anion gap acidosis. Meanwhile, the patient may hyperventilate from fever, pain, or systemic stress, producing respiratory alkalosis. The blood gas can show a pH that is higher than expected because the two disorders partially offset each other.
Another case involves toxic alcohols. These substances can generate acids that raise the anion gap, leading to severe metabolic acidosis. If the patient is also breathing rapidly due to physiologic stress, agitation, or central nervous system effects, a mixed pattern may appear. The result is a high-risk clinical scenario that requires prompt recognition.
Salicylate poisoning is a classic mixed disorder. It often causes respiratory alkalosis early because the toxic exposure stimulates the respiratory center. Later, a high anion gap metabolic acidosis develops as acid metabolites accumulate. The combination can produce a deceptively near-normal pH, which is why blood gas analysis and serum chemistry must be reviewed together.
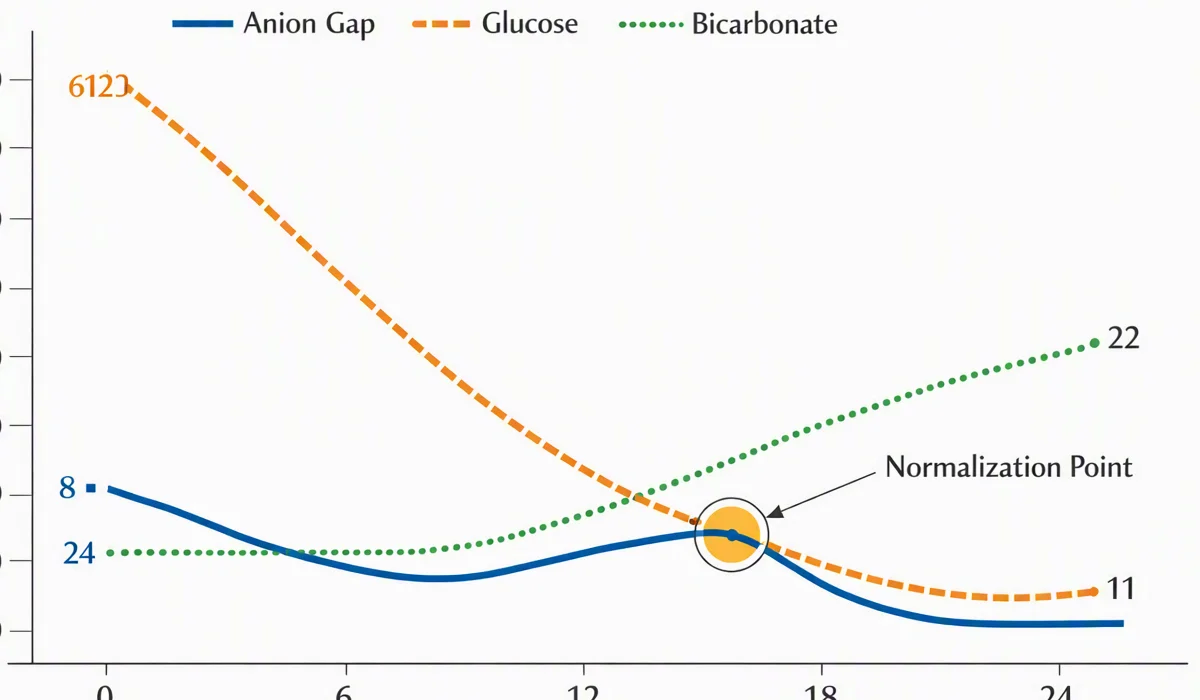
These patterns show why laboratory interpretation matters. A patient can be severely ill even when one number seems only mildly abnormal. The anion gap formula, pH, pCO2, and clinical presentation all need to be interpreted together to identify the correct diagnosis.
When to Obtain Immediate Clinical Evaluation
Specific findings should require urgent clinical evaluation, notably when they present alongside an elevated anion gap. Serious lab values such as a very low bicarbonate, significantly abnormal pH, or markedly elevated serum anion gap may indicate a potentially fatal metabolic disturbance. interpret high anion gap These results need immediate clinical attention rather than routine follow-up.
Clinical signs matter just as much as lab results. Altered mental status, confusion, extreme weakness, rapid breathing, chest discomfort, or inability to stay awake can all signal a serious acid-base disorder. If the patient is not protecting the airway or cannot provide a reliable history, the urgency increases.
Shock is another important warning sign. Poor perfusion can worsen lactic acidosis and rapidly destabilize the acid-base status. In that setting, the elevated anion gap may reflect a serious underlying cause such as sepsis, toxic ingestion, or organ failure. Urgent evaluation is needed because these conditions can progress quickly.
In short, a mixed acid-base disorder with a high anion gap is not something to ignore. It can represent a critical electrolyte disorder or systemic illness that needs prompt diagnosis and treatment.
Frequently Asked Questions
What is considered an elevated anion gap?
An elevated anion gap is a higher-than-expected result on an anion gap calculation using serum sodium, serum chloride, and serum bicarbonate. The exact cutoff can vary by laboratory because reference ranges differ, but a clearly increased value suggests excess unmeasured anions and raises concern for high anion gap metabolic acidosis. Always interpret the number with the rest of the blood gas and serum chemistry results.
How does a mixed acid-base disorder differ from a simple disorder?
A simple disorder has one primary acid-base problem with an appropriate compensatory response. A mixed acid-base disorder has two or more separate processes happening at the same time, such as metabolic acidosis plus respiratory alkalosis. The clue is often that the pH, pCO2, and bicarbonate do not fit the expected pattern for a single disorder.
Can a patient have both metabolic acidosis and respiratory alkalosis at the same time?
Yes. This is a classic mixed acid-base disorder. It can happen in sepsis, salicylate poisoning, liver disease, or other situations where the body is producing acid while also causing rapid breathing. In these cases, the pCO2 may be less than predicted for routine compensation, and the pH may appear less disturbed than the severity of illness would suggest.
What conditions most commonly cause a high anion gap?
Typical causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions all produce or hold onto acids that increase the anion gap. The best differential diagnosis comes from integrating the anion gap with the arterial blood gas, clinical findings, and other laboratory interpretation clues.
How do you calculate and interpret the anion gap in lab results?
The anion gap formula uses serum sodium minus the sum of serum chloride and serum bicarbonate. Anion Gap Calculator can streamline that calculation and minimize calculation errors. Once you have the result, evaluate it alongside the expected compensation using Winter's formula, review the pH and pCO2, and look for signs of a mixed disturbance. Interpretation works best when the calculated value is matched with the patient’s symptoms and underlying cause rather than viewed alone.