What Is the Anion Gap and Why Does It Matter So Much in Shock?
The anion gap is a practical way to identify hidden acids in the blood and to separate causes of metabolic acidosis during shock. In clinical practice, it is part of a broader acid-base interpretation that starts with the electrolytes in a standard serum chemistry panel. When tissue oxygen delivery drops, the body may shift toward anaerobic pathways and produce acid, making the anion gap a useful diagnostic clue in undifferentiated shock.
In shock, the anion gap can be significant because it can point toward a perfusion problem, a toxic exposure, or another secondary cause of metabolic derangement. A rising gap often suggests unmeasured anions are accumulating, while a normal gap may indicate bicarbonate loss or a different acid-base disorder. Either way, the number should be interpreted in the context of hemodynamic instability, resuscitation status, and the rest of the clinical assessment.
A useful way to think about the anion gap is as a laboratory marker that narrows the differential. It does not diagnose shock by itself, but it can help identify whether the acid-base disorder is more consistent with lactic acidosis, ketoacidosis, renal failure, toxic alcohols, or another process. In critical care, that distinction can alter the next step quickly.
How to Operate an Anion Gap Calculator Correctly
An anion gap calculator is only as reliable as the numbers entered into it. The computation usually depends on serum sodium, serum chloride, and serum bicarbonate, which are obtained from the electrolyte panel. Because the output can guide urgent decisions, the numbers should be checked for alignment with the broader serum chemistry and the clinical picture.
Most calculators use a standard formula that compares measured cations and anions. If the result seems surprising, first verify the lab values and confirm whether the bicarbonate is from the chemistry panel rather than a blood gas. Even small changes in chloride or bicarbonate can change interpretation, especially in a patient with evolving shock and ongoing resuscitation.
To use the calculator correctly, consider these steps:
- Confirm the electrolyte panel is current and not outdated. Use the identical set of values from one blood draw when possible. Check whether albumin is low, since that can mask a real gap. Compare the result with the arterial blood gas and lactate. Interpret the number as part of acid-base interpretation, not in isolation.
The anion gap calculator is especially helpful when the clinical question is whether the patient’s acidosis indicates unmeasured acids or another pattern. In shock, this can support rapid bedside reasoning, but it should never replace clinical assessment or trend monitoring.
What Does a High Anion Gap Suggest in Shock?
A high anion gap in circulatory collapse usually points to accumulation of acids or toxins. The most common cause in unstable patients is lactic acidosis, which often reflects tissue hypoperfusion. When perfusion and oxygenation are inadequate, cells shift to anaerobic metabolism, generating lactate and driving the gap upward.
This pattern is common in sepsis, hemorrhage, cardiogenic shock, and other states with impaired perfusion. The anion gap serves as a valuable diagnostic clue because it may rise before the clinical picture fully declares itself. In a patient with metabolic acidosis and hemodynamic instability, a high gap should raise concern for ongoing oxygen debt and inadequate resuscitation.
That said, a high anion gap does not automatically mean the cause is lactate. It only indicates that unmeasured acids are present. The next step is to match the lab pattern with the story: infection, hypoperfusion, renal dysfunction, diabetic decompensation, or ingestion. In critical care, the value is strongest when combined with the arterial blood gas, lactate, and bedside findings.
In shock, a rising anion gap often signals worsening perfusion deficit, but the cause still needs targeted identification.
Ways to Differentiate High Anion Gap Acidosis Causes?
When a high gap is detected, the primary aim is to identify the underlying secondary cause. During shock states, the leading contenders include ketoacidosis, renal insufficiency, toxic alcohol exposure, and salicylates. Each follows a different treatment path, so the pattern on the labs and the history matter.
Ketoacidosis can happen in diabetes, starvation, or alcohol-related states and often presents with an elevated gap plus low serum bicarbonate. Renal insufficiency can also produce a high gap because acid clearance is impaired. With toxic alcohol ingestion, the gap may be high early, sometimes before an osmolar gap closes in, and the patient may have neurologic findings or unexplained acidosis. Salicylates can cause a mixed acid-base disorder, often combining respiratory alkalosis with metabolic acidosis.
Useful anion gap in chronic kidney disease clues for differentiation include:
- History of diabetes, fasting, or alcohol use for ketoacidosis Established kidney disease, low urine output, or rising creatinine for renal failure Exposure history, altered mental status, or visual symptoms for toxic alcohols Tinnitus, rapid breathing, or mixed respiratory findings for salicylates
In shock, these causes may coexist with lactic acidosis. As an example, a septic patient with renal dysfunction can have more than one acid-base disorder at once. That is why the high anion gap should always trigger broader diagnostic reasoning rather than a single-track conclusion.
What Is a Normal Anion Gap Suggest in Shock?
A typical anion gap does not rule out serious acidosis in shock. It may suggest a non-gap metabolic acidosis, which often results from bicarbonate loss rather than accumulation of unmeasured acids. In the unstable patient, this can occur with intestinal losses, kidney tubular dysfunction, or chloride-heavy fluid administration causing chloride excess.
Normal-gap acidosis is important because it can occur alongside shock-related hypoperfusion. For example, a patient may have received substantial chloride-containing fluids during resuscitation and acquire a non-gap metabolic acidosis even as the initial perfusion deficit resolves. In other cases, diarrhea or renal tubular dysfunction may be the primary acid-base disorder while shock is the overall clinical context.
Never assume a normal gap means the situation is benign. It may simply mean the current problem is not accumulation of unmeasured acids. The bicarbonate can still be low, the pH can still be acidemic, and the patient can still have marked organ stress. Always assess the arterial blood gas, clinical trend, and response to resuscitation.
How Can Albumin Levels Affect Anion Gap Interpretation?
Hypoalbuminemia may cause the anion gap look falsely normal or just slightly high. Albumin is a key unmeasured anion, so when it is low, the measured gap narrows even if clinically important acids are present. This is especially relevant in critical illness, where low albumin is common and can distort acid-base balance interpretation.
Albumin correction can help adjust the gap upward when albumin is low. That adjustment is important because an uncorrected result can miss a true high-gap process. In a patient with shock, this can slow the detection of lactic acidosis or another acid-base disorder that needs urgent attention.
Think about albumin correction when the result does not fit the patient’s condition. If the patient appears severely ill but the gap is “normal,” low albumin may be hiding the abnormality. Correcting for albumin gives a more accurate picture of acid-base balance and helps distinguish a genuine normal-gap state from a masked high-gap state.
In practice, albumin should be checked alongside the anion gap calculator result, the serum bicarbonate, and the arterial blood gas. That combined view is more informative than any single number.
Which Further Labs Can Help Assess Shock & Acid-Base Status?
The anion gap is merely one piece of the acid-base picture. Within shock, several further labs help define the problem and direct resuscitation. The main are lactate, arterial blood gas, base deficit, and serum ketones.
Lactate is especially helpful because it mirrors the severity of hypoperfusion and the degree of oxygen debt. An elevated lactate supports lactic acidosis, though the exact source still requires clinical interpretation. The arterial blood gas displays pH, PaCO2, and bicarbonate, helping identify whether the patient has a pure metabolic acidosis or a mixed disorder with respiratory compensation. Base deficit provides another way to quantify metabolic acidosis and can help follow response over time. Serum ketones are important when ketoacidosis is possible.
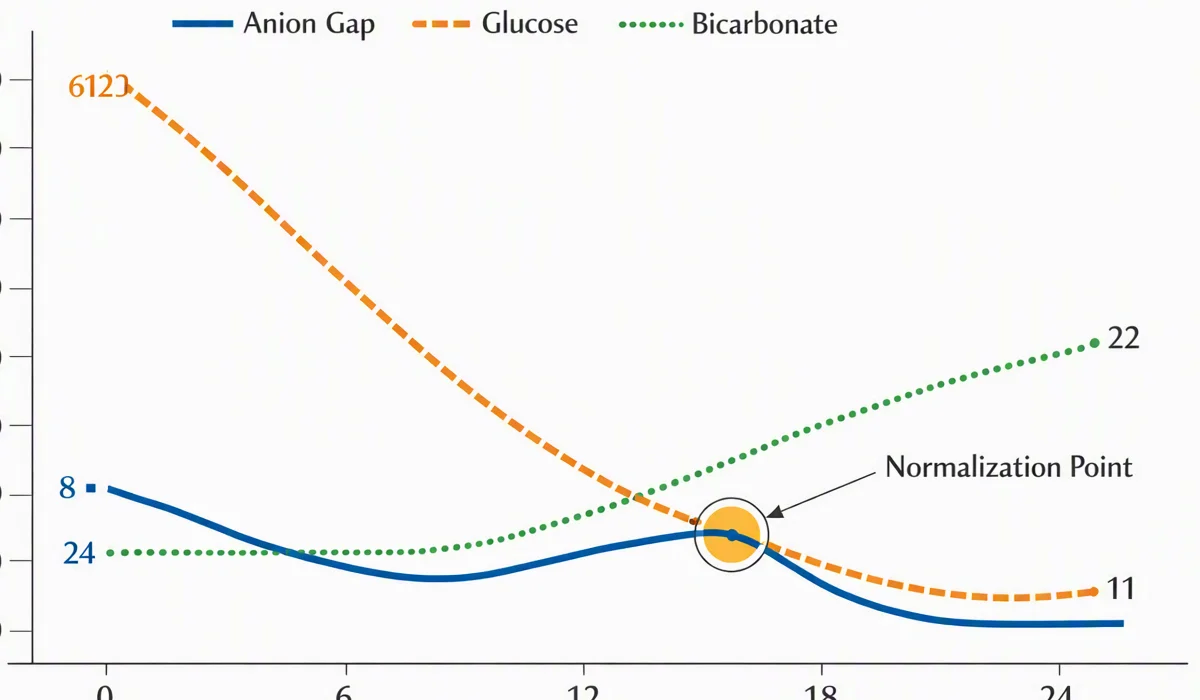
Other supportive data may include creatinine, glucose, osmolar gap if toxic alcohols are a concern, and repeat electrolytes to monitor the changing serum chemistry. In critical care, a single snapshot is rarely enough. The broader lab pattern is the best way to connect the anion NAGMA differential diagnosis gap to the actual cause of shock.
When to Recheck the Anion Gap in Shock Cases?
Reassess the anion gap when the patient is receiving active emergency treatment, when the cause of shock is still being clarified, or when treatment is underway and you need serial assessment. Ongoing monitoring is especially useful if the initial gap is high, if lactate is elevated, or if the clinical response is hard to interpret.
A decreasing gap can be a comforting sign that the metabolic derangement is gettting better. In lactic acidosis, for example, the gap may fall as perfusion improves and oxygen delivery is improved. In ketoacidosis, it often narrows as insulin and fluids resolve the metabolic process. In toxic ingestion, the pattern may evolve otherwise, but trend monitoring still helps show whether treatment is working.
Reassess sooner if the patient worsens, if new laboratory data do not match the bedside picture, or if a mixed disorder is suspected. In shock, the anion gap is most useful when it is paired with serial clinical assessment and a clear understanding of the compensatory response.
Frequent Mistakes When Interpreting Anion Gap in Shock
A typical error is lab error. A broken-down sample, specimen mix-up, or outdated value can result in incorrect interpretation. Another common mistake is failing to recognize mixed acid–base disorders, which are frequent in shock and can mask the true process.
Failing to consider albumin adjustment is an all-too-common error. A low albumin can make a concerning high-gap acidosis appear less obvious than it really is. The reverse can also occur: a patient can have both lactic acidemia and chloride-related acidosis, which may somewhat cancel out each other and create a deceptively modest gap.
The delta gap can be useful if a mixed disorder is considered. It evaluates the change in anion gap with the change in bicarbonate and can indicate whether there is an concurrent alkalosis or a separate non-gap acidosis. This is helpful in unclear shock, where more than one process may be occurring at the same time.
Further mistakes include missing the clinical context, forgetting that shock itself may cause lactic acidosis, and depending on one isolated value in place of the full pattern. Good acid-base interpretation depends on the electrolyte panel, arterial blood gas, lactate, and bedside hemodynamics to be reviewed together.
FAQ: Anion Gap in Shock
What does a high anion gap mean in shock?
An elevated anion gap in shock usually means unmeasured acids are building up, most often from lactic acidosis due to tissue hypoperfusion. It can also reflect ketoacidosis, renal failure, toxic alcohols, or salicylates, so the result should be interpreted with the clinical picture and other labs.
Can shock cause a normal anion gap metabolic acidosis?
Absolutely. Shock can occur with normal anion gap metabolic acidosis, especially if chloride-rich fluids are given during resuscitation or if there is another cause such as diarrhea or renal tubular acidosis. A normal gap does not eliminate a significant acid-base disorder.
How does lactate affect the anion gap?
Lactate is an unmeasured anion, so when it rises it can increase the anion gap. Elevated lactate often reflects inadequate oxygen delivery, tissue hypoperfusion, or sepsis-related metabolic stress.
Why should albumin be considered when interpreting the anion gap?
Albumin is a major unmeasured anion. If albumin is low, the anion gap may appear artificially normal or only slightly elevated. Albumin correction helps uncover hidden metabolic acidosis, especially in critical illness.
What labs should be checked with an anion gap calculator in shock?
Along with the Anion Gap Calculator result, check lactate, arterial blood gas, base deficit, serum ketones, and repeat electrolytes including serum bicarbonate. These tests help define the acid-base disorder and distinguish lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and other causes.