What’s the Anion Gap?
The anion gap is a computed value used to evaluate acid-base balance and detect certain problems in the body’s electrolytes. It looks at the main measured positive and negatively charged ions in plasma or serum to approximate the presence of unmeasured ions. In everyday clinical use, the anion gap is a valuable clue in assessing an acid-base disorder, especially metabolic acidosis.
Because routine blood chemistry tests do not measure every ion in blood, the anion gap assists in complete part of the picture. A increased or low result does not diagnose a condition by itself, but it can shape the next step in clinical interpretation. That is why many clinicians use an anion gap calculator to quickly calculate anion gap values from a patient’s lab values.
In simple terms, the anion gap reflects the difference between measured cations and measured anions. The most typical measured cation is sodium, and the main measured anions are chloride and bicarbonate. This is why the test is so closely tied to an electrolyte panel and broader serum electrolytes review.
Formula for Anion Gap
The usual anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Certain labs and clinicians also use variations that include potassium, but the most widely used formula omits it. In practice, the calculation usually relies on serum sodium, serum chloride, and serum bicarbonate. These represent the core values used in an anion gap calculation and in many online calculator tool choices.
If you use an anion gap calculator, you just enter the relevant serum electrolytes. The tool then does the math automatically and returns a result that can support medical interpretation. A calculator is especially useful when reviewing multiple labs or when you want a quick check on a lab result during a metabolic acidosis workup.
Below is the basic logic behind the formula:
- Sodium acts as the largest measured cation in the blood. Chloride and bicarbonate are the main measured anions. The gap represents unmeasured anions such as proteins, phosphate, sulfate, and organic acids.
Because of that, the result can help identify whether an electrolyte imbalance is being driven by excess acid in the body, loss of bicarbonate, or another process affecting blood chemistry.
Stepwise Demonstration of Computing Anion Gap
Below is a simple example calculation based on typical lab values:
- Sodium = 140 Chloride = 104 Bicarbonate = 24
Now apply the equation:
140 - (104 + 24) = 140 - 128 = 12
The calculated anion gap is 12. According to the lab’s normal range, this may be considered inside the usual anion gap range. Always check the result with the specific lab’s range, because the normal interval can vary somewhat by method and analyzer.
A further example can help show how the result changes:
- Na = 138 Chloride = 98 Bicarbonate = 16
138 - (98 + 16) = 138 - 114 = 24
This indicates an high anion gap and may suggest a high anion gap process, especially if the patient has symptoms or other abnormal labs. In real-world use, this kind of result leads to closer review of the clinical context and additional testing.
What Does a High Anion Gap Signify?
A high anion gap often suggests there are extra unmeasured acids in the blood. The most common clinical concern is metabolic acidosis, where acid collects or bicarbonate is depleted faster than it can be replaced. This is a key reason the anion gap is so important in an acid-base disorder evaluation.
Common causes of a high anion gap include:
- Lactic acidosis, where lactate rises because of poor oxygen delivery, shock, severe illness, or certain medications Ketone-related acidosis, which can occur with diabetes, starvation, or heavy alcohol use Poisoning from toxic alcohols, including substances such as methanol or ethylene glycol Impaired kidney function or other conditions that reduce acid clearance
These causes are often reviewed during a workup for metabolic acidosis. The anion gap does not identify the exact cause on its own, but it narrows the differential diagnosis. For example, a very elevated value in the setting of illness may point toward lactate-related acidosis, while a patient with diabetes and high glucose may raise concern for ketoacidosis.
It is also important to remember that a high result is not always due to one dramatic diagnosis. Sometimes medication effects, dehydration, or mixed disorders can alter the final clinical interpretation. That is why the anion gap should be read alongside the full picture of electrolyte levels, symptoms, and other test results.
What Is a Reduced Anion Gap Indicate?
A reduced anion gap is more unusual than a elevated one, but it can still be medically important. One major cause is hypoalbuminemia, or low albumin. Because albumin is a negatively charged protein, a decrease in albumin can lower the measured gap even if nothing else is wrong with the acid-base balance.
Other possible low anion gap causes include:
- Laboratory error or specimen handling problems Alterations in proteins associated with multiple myeloma Substantial increases in unmeasured cations Measurement issues affecting the measured electrolytes
Among these, laboratory error is one of the initial things to consider because it is common and easy to recheck. If the value remains low, then albumin level and other blood chemistry markers should be reviewed carefully. In some cases, a low gap may be the first clue to multiple myeloma or another protein disorder.
Low values do not always signal urgent disease, but they should not be ignored. A patient with persistent low anion gap findings may need further evaluation, especially if there is anemia, kidney issues, bone pain, or other signs that fit a protein-related disorder.
Typical Anion Gap Range with Correction for Albumin
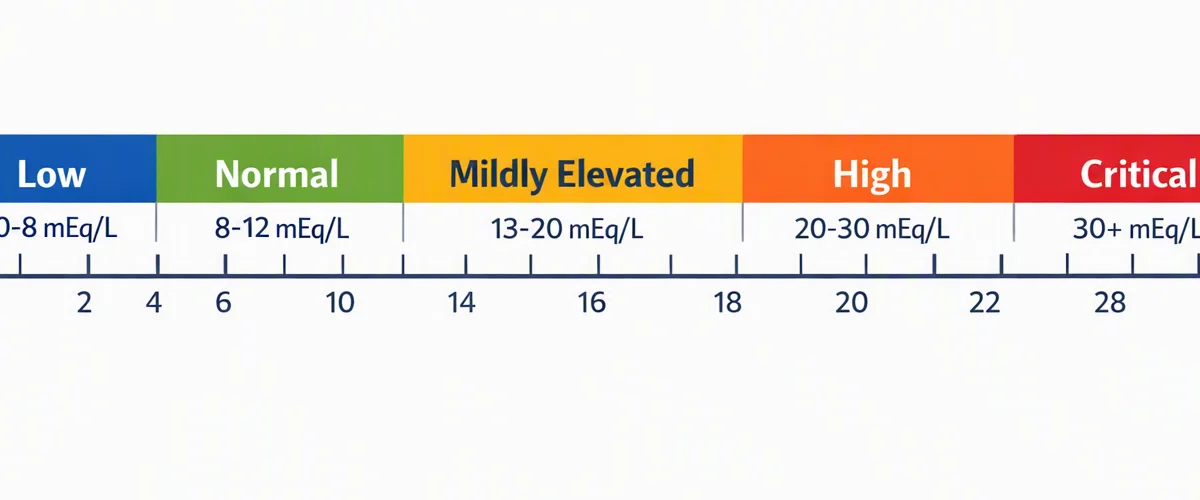
The normal range for the anion gap varies with the laboratory method, but a commonly used range is approximately 8 to 12 mEq/L when potassium is excluded. Certain laboratories use different cutoffs, so the printed range on the report should always guide interpretation. A result may be within range in one lab and slightly high in another.
Because albumin affects the result, many clinicians apply an albumin correction. This matters when interpreting the calculated anion gap in patients with low protein levels. If albumin is reduced, the anion gap may appear falsely reassuring unless corrected.
A common correction approach is to add about 2.5 mEq/L to the anion gap for every 1 g/dL decrease in albumin below 4.0 g/dL. For example, if albumin is 2.0 g/dL, the correction would be about 5 mEq/L. This can change the interpretation significantly, especially when evaluating a possible acid-base disorder.
Why does this matter? Albumin is one of anion gap in chronic kidney disease the major unmeasured anions in the blood. When albumin is low, the body has fewer negative charges to “balance” the measured cations, so the apparent anion gap drops. Correcting for albumin makes the number more accurate and improves clinical decision-making.
In practice, the best approach is to look at the raw value, the albumin level, and the corrected value together. That gives a clearer picture than relying on a single number alone.
Frequently Asked Concerns Concerning Anion Gap Calculation
The anion gap is a blood test-based calculation, but it is not a single test. It is calculated from the electrolyte panel and used to help understand the results of everyday chemistry testing. Clinicians use it as part of broader clinical use in evaluating acid-base disorders, especially metabolic acidosis.
When should someone pay close attention to the number? A high or reduced result may carry more weight if the patient has symptoms such as vomiting, confusion, rapid breathing, weakness, or signs of dehydration. In those settings, the anion gap can back up a diagnosis or guide further testing.
Is the number enough by itself? No, it is not. The value is a diagnostic tool, not a final answer. It should be read with the rest of the blood chemistry, including glucose, kidney function, albumin, and sometimes lactate or ketones. The goal is to interpret laboratory values in context rather than in isolation.
Because the calculation is so straightforward, many clinicians and patients use an anion gap calculator to avoid arithmetic mistakes and speed up review. This is especially valuable when comparing repeated results over time or checking whether a change is real versus due to shifting electrolytes.
When to Use an Anion Gap Calculator
An anion gap calculator is especially useful when you want a rapid, reliable calculate anion gap result from a set of serum electrolytes. It reduces manual errors and gives a quick check during routine review of a lab result. The calculator tool is particularly useful when multiple values need to be assessed quickly in a busy clinical setting.
Common situations where a calculator helps include:
- Reviewing an abnormal electrolyte panel Screening for metabolic acidosis or other acid-base disorders Checking whether a result fits normal anion gap expectations Aiding medical interpretation when albumin is low Performing quick screening for possible elevated or decreased gap states
The calculator is not a substitute for clinical judgment, but it is a useful diagnostic tool. It helps double-check the arithmetic, review values over time, and apply the right albumin correction when needed. This improves confidence in the final interpretation of the lab data.
Using an anion gap calculator is also helpful when teaching students or explaining the result to patients. Since the formula is simple, the tool makes it easier to connect the numbers on the page to the underlying physiology of acid-base balance.
Frequently Asked Questions
How do you calculate anion gap from lab values?
Use the anion gap formula: sodium minus the sum of chloride and bicarbonate. In formula form, it is anion gap = sodium - (chloride + bicarbonate). This is the standard way to calculate anion gap from routine lab values on a blood chemistry panel.
What is the normal anion gap range?
The normal values depend on the laboratory’s reference range, but a common range is about 8 to 12 mEq/L when potassium is not included. Always use the range printed with the test result, since methods and analyzers can differ.
Why is albumin used to correct the anion gap?
Albumin is a major unmeasured anion in the blood, so low albumin can reduce the measured value. Albumin correction helps make the calculated anion gap more precise, especially when hypoalbuminemia is present.
What leads to a high anion gap?
A high anion gap is often caused by metabolic acidosis from additional acids in the body. Common causes include lactic acidosis, ketoacidosis, and toxic alcohol ingestion. Kidney failure and other acid-retaining conditions can also elevate the gap.
Can a low anion gap be a sign of a serious problem?
Yes, sometimes it can. A low anion gap may result from lab error, but it can also be linked to hypoalbuminemia AG in CKD patients or conditions such as multiple myeloma. If the finding persists, it deserves careful review along with the rest of the serum electrolyte data and the patient’s clinical picture.