Understanding the Anion Gap?
The anion gap is a derived value based on common electrolytes in a blood test. It helps clinicians evaluate acid-base balance and identify likely sources of unmeasured anions in the blood. In practice, the anion gap is a helpful diagnostic aid when reviewing serum chemistry results during a clinical assessment.
Most often, the calculation uses sodium and chloride, along with bicarbonate. Because these lab values mirror the balance of charged particles in the bloodstream, the anion gap can help identify an underlying metabolic disorder such as metabolic acidosis. A blood test may look otherwise routine, but the anion gap can reveal important clues about an electrolyte imbalance.
Although the name suggests a gap, it is not a true empty space. Instead, it is an estimate of the difference between measured cations and measured anions. That makes it an key concept in clinical interpretation of lab results and a standard part of the metabolic acidosis workup.
Anion Gap Overview and Input Values
The formula for the anion gap is usually based on 3 main laboratory values: Na, Cl, and HCO3. Many medical professionals use an Anion Gap Calculator to speed up the calculation and limit manual errors when evaluating a lab result.
The basic formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
Some forms of the calculation also include K. When potassium is added, the equation becomes:
Anion gap = (serum sodium + potassium) − (serum chloride + serum bicarbonate)
Both methods are used in clinical practice, but the potassium-inclusive version is less common because potassium usually contributes only a limited amount to the final number. What matters most is to know which method your laboratory or clinician uses so the interpretation stays uniform.
An anion gap calculator is especially useful when comparing serial results, tracking subtle shifts in lab values, or checking whether an elevated result may indicate a genuine acid-base problem. It offers a fast estimate of the anion gap using standard laboratory inputs and can support broader clinical interpretation.
How to Work out the Anion Gap Step-by-Step
To work out the anion gap by hand, you need three key values: serum sodium, serum chloride, and serum bicarbonate. The method is easy to follow and can be used to verify a calculator result.
Use these steps:
- First, start with the serum sodium value. Add serum chloride and serum bicarbonate together. Take away that total from the sodium value.
Here is a clear calculation example:
- Serum sodium = 140 Serum chloride = 102 Serum bicarbonate = 24
Then use the formula:
140 − (102 + 24) = 140 − 126 = 14
In this example, the anion gap is 14. Depending on the lab’s reference range, this may be normal or only mildly elevated. A single number should always be interpreted alongside the full clinical picture, including symptoms, the broader serum chemistry panel, and other markers of acid-base status.
Some clinicians also review whether the result suggests a likely metabolic acidosis, especially if the bicarbonate is low. In that context, the anion gap can guide the next steps in the differential diagnosis.
Normal Anion Gap Range and Lab References
The expected range for the anion gap can vary depending on the laboratory, the analyzer, and whether potassium is included. For that reason the reported reference range matters more than any one universal cutoff.
In general, many labs use a reference range that is usually around the low teens, but the exact number depends on the method and local lab variation. Because of this variation, two people with the same lab values may receive slightly different interpretations depending on where the blood test was processed.
Albumin also affects the expected value. Since albumin is a major negatively charged protein in the blood, lower albumin can reduce the measured anion gap even when the underlying acid-base picture is abnormal. That is why the normal range must be considered in context rather than treated as a fixed universal value.
When reviewing a lab result, it is best to compare it with the specific reference interval printed by the laboratory. This helps ensure that the assessment reflects the correct assay and avoids overcalling a result as abnormal.
What High and Reduced Anion Gap Results Mean
A elevated anion gap often suggests a buildup of acidic substances in the blood. This result is especially important in metabolic acidosis, where bicarbonate is used up as the body cushions acid. In that scenario, the elevated gap points toward a problem beyond basic bicarbonate reduction.
A low anion gap is uncommon, but it can nevertheless be clinically meaningful. One common cause is hypoalbuminemia, because albumin helps form the normal unmeasured anion pool. Other causes may include lab issues or abnormal proteins in the blood.
Either high or low values should be interpreted as part of a wider clinical assessment. A single lab value almost never provides the entire answer. Instead, the anion gap acts as a clue that helps sharpen the differential diagnosis and guide a more specific evaluation of the patient’s acid-base status.
Causes of elevated anion gap metabolic acidosis
If the anion gap is increased, clinicians often evaluate causes of high anion gap metabolic acidosis. Such disorders increase the amount of hidden acids in the bloodstream and alter the balance of electrolytes.
Typical causes are:
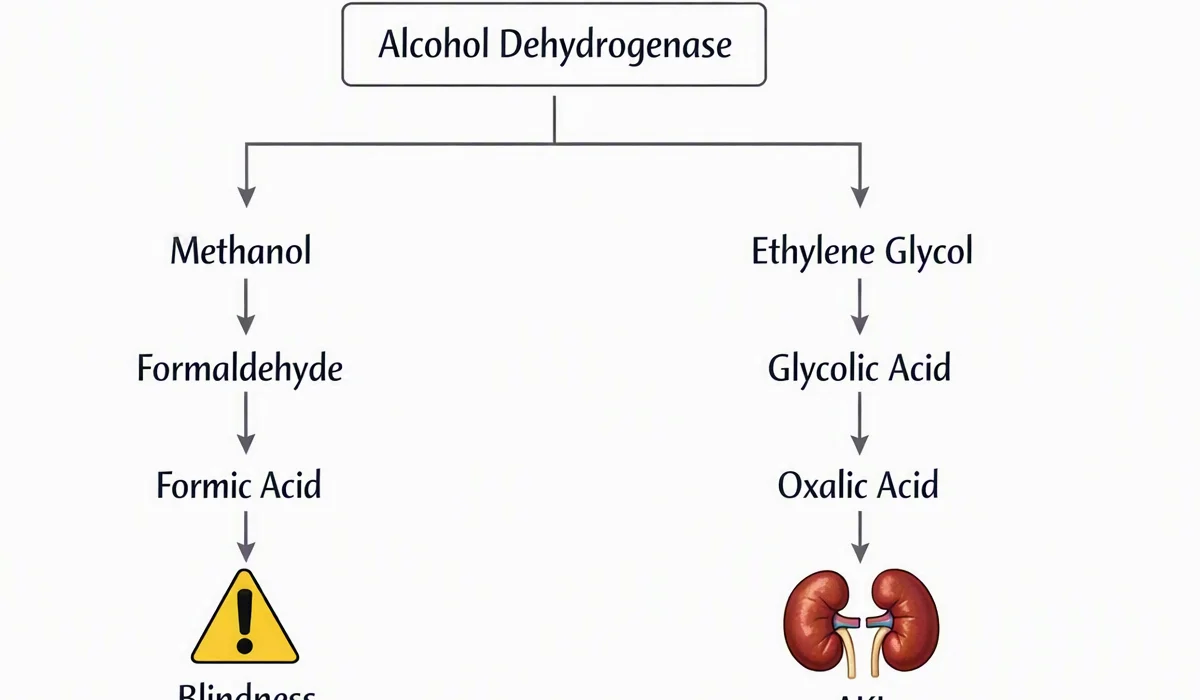
- Lactic acid buildup, where lactate accumulates during tissue hypoxia, shock, seizure, or severe illness. Ketone acidosis, that can occur in diabetes, starvation, or heavy alcohol use. Renal failure, because the kidneys cannot clear acids effectively. Alcohol toxins, like methanol or ethylene glycol, which create dangerous acid metabolites.
Such findings matter because they can signal a serious metabolic disorder requiring urgent treatment. In a metabolic acidosis workup, the anion gap helps distinguish between acid loss and acid accumulation. A higher gap often suggests that the body is dealing with added acids rather than simply losing bicarbonate.
Clinicians may also use the anion gap as part of a broader differential diagnosis. For example, in someone with altered mental status and an unexplained acid-base disorder, the result may help prioritize toxic ingestion, renal impairment, or severe infection.
Causes of Low Anion Gap
A low anion gap can occur for several reasons, and it should not be overlooked. The main explanation is hypoalbuminemia, since less albumin means fewer negatively charged proteins in circulation. This alters the measured balance and can lower the calculated result.
Other possible causes include:
- Hyperalbuminemia, though this is less often a true clinical issue than a testing-related or concentration-related finding. Multiple myeloma, where abnormal proteins can alter the serum charge balance. Paraproteins, which may function as positively charged proteins and lower the calculated gap. Lab error, including specimen or measurement problems that affect the result.
Because a low result can sometimes reflect a testing issue rather than a disease process, it is wise to evaluate the sample quality and repeat the test if needed. In clinical practice, a low anion gap may be the initial sign to an abnormal protein state or an electrolyte pattern that deserves more careful evaluation.
Adjusting the Anion Gap for Albumin
Albumin correction is an important step when interpreting the anion gap, especially if serum albumin is low. As albumin contributes greatly to the normal anion gap, a reduced albumin level can make the measured value appear lower than expected.
The goal of a corrected anion gap is to estimate what the result would be if albumin were normal. This gives a more accurate view of the underlying charge balance in the blood and improves anion gap estimation in patients with abnormal protein levels.
Different formulas exist, but the general principle is the same: apply a correction factor based on the albumin level. When albumin is low, the corrected number may reveal a masked high anion gap that was concealed by the reduced protein concentration.
This step is especially useful in patients with serious illness, malnutrition, chronic disease, or inflammation, where albumin is often below normal. Without albumin correction, clinicians may downplay the severity of an acid-base disturbance and overlook an important part of the diagnosis.
How Clinicians Apply the Anion Gap in Acid-Base Interpretation
The anion gap is one piece of a larger acid-base puzzle. Clinicians use it to help sort acid-base disorders, evaluate suspected metabolic acidosis, and interpret the result with other laboratory findings. It is infrequently used alone.
For example, if a patient has low bicarbonate and a high anion gap, that pattern supports an acid buildup process such as lactic acidosis, ketoacidosis, renal failure, or toxic alcohol ingestion. If bicarbonate is low but the gap is normal, the cause may be another condition, such as gastrointestinal bicarbonate loss or renal tubular problems.
The anion gap is also helpful when reviewing metabolic alkalosis or respiratory disorders. In those settings, clinicians look at the entire pattern of pH, carbon dioxide, bicarbonate, and electrolytes to understand whether the body is compensating appropriately. The anion gap may provide extra context even when it is not the main abnormality.
Another helpful idea is the delta gap, which evaluates the change in the anion gap with the change in bicarbonate. This helps spot mixed acid-base disorders and can reveal whether more than one process is occurring at the same time. In complex cases, the delta gap brings depth to the clinical interpretation and enhances diagnostic accuracy.
Overall, the anion gap supports acid-base balance assessment by turning routine lab values into actionable insight. It is a practical tool for interpreting a blood test, guiding the workup, and explaining the clinical significance of electrolyte shifts.
Frequently Asked Questions About the Anion Gap Calculator
What is the anion gap calculator used for?
The anion gap calculator is used to estimate the anion gap from routine lab values and aid clinical interpretation of acid-base status. It helps detect possible causes of metabolic acidosis, review electrolyte imbalance, and inform the differential diagnosis when a blood test shows abnormal serum chemistry results.
How do you calculate the anion gap formula?
The standard anion gap formula is serum sodium − (serum chloride + serum bicarbonate). Some versions also include potassium, but the sodium-based formula is most commonly used. An online calculator or manual calculation can both give the result, as long as the same lab values are Check out this site used consistently.
What is a normal anion gap range?
The normal anion gap depends on the laboratory’s reference range and the analyzer used. Because of laboratory variation, the exact normal range can differ from one lab to another. Albumin level also affects the expected result, so the reference interval should always be reviewed alongside the lab report.
Why is the anion gap high in metabolic acidosis?
The anion gap is high in metabolic acidosis when unmeasured acids accumulate in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These conditions increase unmeasured anions and lower bicarbonate, producing a higher calculated gap.
Should the anion gap be corrected for albumin?
Certainly, correction for albumin can be helpful when blood albumin is reduced. As albumin plays a role in the normal anion gap, low albumin can hide a true elevation. A corrected anion gap gives a more accurate view of charge balance and can enhance interpretation in difficult cases.