What Is the Anion Gap?
The anion gap is a computed value used to aid in evaluating acid-base balance and recognize certain types of electrolyte imbalance. It comes from a typical serum chemistry panel and weighs measured cationic ions with measured negative ions in the blood. In everyday use, it allows clinicians identify a hidden metabolic derangement that may not be apparent from symptoms alone.
The classic calculation uses serum sodium, serum chloride, and serum bicarbonate. These electrolytes are part of the body’s buffering system, which helps maintain stable pH. When the balance shifts, the anion gap can elevate or stay normal depending on the underlying cause of the problem.
One reason the anion gap is useful is that it acts as a diagnostic clue during a medical evaluation. A changed gap can indicate a specific acid-base disorder, especially metabolic acidosis. It is not a diagnosis by itself, but it can sharpen the differential diagnosis and direct follow-up testing.
The normal reference range varies somewhat by laboratory because of differences in measurement methods and reporting. That is why the lab’s own result range matters more than a single universal number. Still, the basic concept remains the same: the anion gap reflects the difference between measured ions and can reveal an anion deficit or an excess of unmeasured acids.
How the Anion Gap Calculator Works
An anion gap calculator is a quick medical utility that uses the standard formula to values entered from a serum chemistry panel. Most calculators use sodium, chloride, and bicarbonate. Others also include potassium, depending on the formula being used and the institution’s preference.
The standard formula is:
Anion gap = sodium - (chloride + bicarbonate)
When potassium is included, the formula becomes:
Anion gap = sodium + potassium - (chloride + bicarbonate)
The calculator gives a calculated value that assists assess whether an acid load is present. In clinical use, this is more than a math exercise. It is a screening tool that can indicate whether a patient may have metabolic acidosis and whether the pattern suggests a elevated-gap or standard-gap process.
Because the result is influenced by measurement technique and lab-specific calibration, the calculator should always be interpreted in context with the rest of the laboratory result. It works best as part of a broader clinical interpretation rather than as a single number.
For example, low bicarbonate with a high gap suggests accumulation of unmeasured acids. Low bicarbonate with a normal gap often suggests a loss of bicarbonate rather than acid accumulation. That distinction is essential to understanding the test.
Anion Gap Metabolic Acidosis: What the Result Indicates
Metabolic acidosis indicates the blood has grown more acidic because bicarbonate has dropped, acid has risen, or both. The anion gap helps categorize the problem into high anion gap metabolic acidosis or normal anion gap metabolic acidosis. This classification gives an important clinical clue about the likely mechanism.
A high anion gap usually points to the presence of unmeasured acids. These acids deplete bicarbonate during buffering, which raises the gap. This pattern often points to problems such as lactic acid buildup, ketone production, kidney dysfunction, or ingestion of certain toxins.
A normal anion gap result does not mean the patient is normal. It usually means bicarbonate has been lost and chloride has risen to maintain electrical neutrality, producing a pattern often called hyperchloremic acidosis. This is a different type of acid-base disturbance and requires a different line of thinking.
Recognizing the pattern matters because the treatment depends on the cause. A patient with high-gap acidosis may need urgent assessment for sepsis, hypoperfusion, diabetes, or toxin exposure. A patient with normal-gap acidosis may need evaluation for gastrointestinal losses, renal tubular defects, or medication effects.
In short, the anion gap is a practical way to identify the biochemical signature of acid-base balance disturbances. It helps clinicians move from a general finding of metabolic acidosis to a more specific investigation of the underlying cause.
How to Calculate the Anion Gap Step-by-Step
Determining the anion gap is simple when you have the primary electrolyte values. The standard procedure use sodium, chloride, and bicarbonate, with additional inclusion of potassium.
- Step 1: Get the serum electrolyte values from the lab report. Step two: Verify the values for serum sodium, serum chloride, and serum bicarbonate. Step 3: Combine chloride and bicarbonate together. Last: Deduct that sum from sodium.
Using the basic formula:
Anion gap = sodium - (chloride + bicarbonate)
If the calculator includes potassium, incorporate it to the sodium value before subtracting the other electrolytes. Potassium is generally a minor component of the formula, but it can a bit change the result.
For example, if sodium is 140, chloride is 102, and bicarbonate is 22, the calculation is 140 - (102 + 22) = 16. If potassium is included and is 4, the calculation becomes 140 + 4 - (102 + 22) = 20.
That number is then reviewed with the lab’s reference range. Some labs consider a upper range normal, while others use a lower one. The key is to interpret the result using the specific reference range attached to the patient’s lab system.
Even when the arithmetic is easy, the meaning is not. The calculated result should always be assessed in the setting of the patient’s symptoms, other test results, and overall clinical interpretation.
Adjusted Anion Gap and Adjustment for Albumin
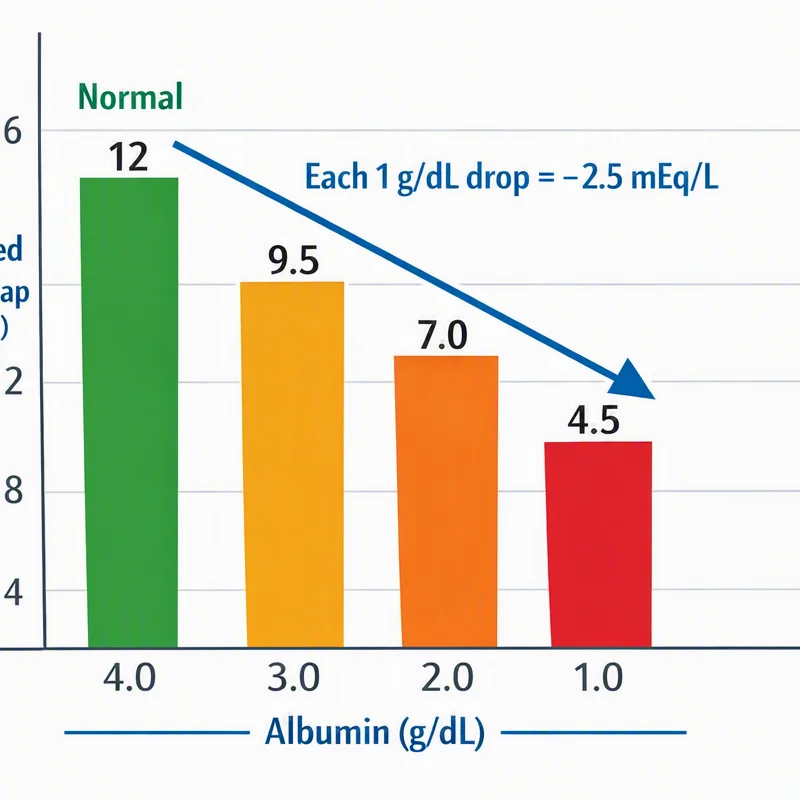
Albumin has a substantial effect on the anion gap because it is one of the chief unmeasured anions in blood. When albumin is low, the measured anion gap may look artificially normal even when a clinically significant acidosis is present. This is why the corrected anion gap is important.
Hypoalbuminemia decreases the baseline gap by lowering the amount of unmeasured negative charge in the plasma. In patients with low albumin, failing to adjust can hide a high-gap process. The correction helps provide a more accurate estimate of the true acid burden.
A commonly used corrected formula applies a small amount to the measured anion gap for every decrease in albumin below the normal range. The exact adjustment may differ by institution, but the principle is the same: low albumin means the observed value may minimize the actual disturbance.
This is why the corrected value is often more clinically meaningful than the raw number. A patient with an apparently normal laboratory result range may still have an elevated corrected gap if albumin is reduced. That can shift the interpretation from normal to concerning for hidden high-gap metabolic acidosis.
Albumin adjustment is especially important when the clinical picture points to serious illness but the uncorrected anion gap does not match. In that setting, the corrected anion gap can reveal an important metabolic problem and strengthen the quality of the diagnostic workup.
Frequent Causes of High Anion Gap Metabolic Acidosis
High anion gap metabolic acidosis occurs when acids accumulate in the body at a faster rate than they can be cleared. The excess acids consume bicarbonate and widen the gap. The main causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion.
Lactic acidosis develops when oxygen delivery or utilization is impaired, leading to lactate elevation. This can happen in shock, severe infection, hypoxia, seizures, or tissue ischemia. Lactate is an key clue because it often signals a serious underlying cause that needs urgent treatment.
Ketoacidosis is commonly related to uncontrolled diabetes, starvation, or alcohol use. In this situation, ketone accumulation raises the acid load. The resulting metabolic derangement may present with nausea, vomiting, abdominal pain, dehydration, or altered mental status.
Renal failure can also lead to a high gap because the kidneys cannot excrete acids effectively. As acid builds up, the anion gap rises and bicarbonate falls. This pattern may appear over time in chronic kidney disease or more abruptly in acute kidney injury.
Toxic alcohol ingestion is a further important cause, especially when the presentation is severe or unexplained. Certain ingestions generate acids that increase the gap and can cause dangerous neurologic, metabolic, and visual complications. When the history is uncertain, the anion gap may become an early warning sign.
These conditions are part of the main differential diagnosis for a high-gap result. The calculator does not identify which one is present, but it helps inform the next tests and the urgency of care.
Common Reasons of Normal Anion Gap Metabolic Acidosis
Normal anion gap metabolic acidosis happens when bicarbonate is depleted and replaced by chloride, maintaining the overall gap within the reference range. This is often called hyperchloremic acidosis because chloride increases as bicarbonate falls.
A frequent cause is diarrhea, which leads to direct gastrointestinal bicarbonate loss. The body compensates by retaining chloride, and the result is a low bicarbonate state with a normal gap. This pattern is often observed in volume depletion as well.
Renal tubular acidosis is another major cause. In this condition, the kidneys fail to acidify urine or conserve bicarbonate appropriately. The result is an acid-base disorder that can persist despite a seemingly ordinary anion gap.
Other causes of normal-gap acidosis may include medication effects, urinary diversion, or certain kidney disorders, but the major teaching point is simple: the presence of acidosis does not always mean the gap is elevated.
In normal-gap states, the chemistry often shows a chloride shift as bicarbonate drops and chloride increases. This compensation preserves electrical neutrality but indicates a real metabolic problem that still needs a cause-specific evaluation.
Clinical Analysis and Next Steps
Reviewing the anion gap is most useful when paired with the rest of the patient’s data. If the result suggests acid-base imbalance, the next step is usually a targeted diagnostic workup. This evaluation may include an arterial gas analysis, lactate level, ketones, kidney function testing, and sometimes toxin screening.
An blood gas assists verify the pH and respiratory compensation. Blood lactate is helpful when lactic acidosis is suspected. Ketones assist check for diabetic or starvation-related ketoacidosis. Kidney studies help identify whether reduced acid excretion is adding to the disorder.
This gap also helps determine the level of urgency. A markedly high result may indicate a possibly serious metabolism-related condition that calls for immediate attention. A typical gap along with low bicarbonate may suggest an alternative process, such as gastrointestinal loss or renal tubular dysfunction.
Clinical interpretation must also take into account complaints such as breathlessness, disorientation, dehydration, throwing up, stomach pain, or evidence of infection. The laboratory result is only a single part of the full picture, but it can be a crucial diagnostic clue that guides the following step in management.
For this reason, the anion gap calculator is best regarded as a screening tool that assists, rather than replaces, medical reasoning. It aids in organizing the differential diagnosis and streamline the evaluation effectively.
Drawbacks of an Anion Gap Calculator
An anion gap calculator is helpful, but it has important drawbacks. The first is variability in lab results. Different analyzers, measurement methods, and reference intervals can generate somewhat different results. This means the same patient may be placed in different result categories according to where the test was processed.
The other drawback is the effect of albumin. Without correction, a decreased albumin level can hide a genuine raised gap. This is one reason the anion gap correction is so crucial in https://anion-gap-chart972.theglensecret.com/do-convulsions-raise-the-anion-gap patients with hypoalbuminemia or severe illness.
Another issue is that the gap does not measure directly every relevant ion. Shifts in unmeasured cations, including ionized calcium, may affect interpretation in certain situations. The calculator also does not determine whether the acidosis is acute or chronic, nor does it disclose the exact underlying cause.
Most importantly, the number must be anion gap in chronic kidney disease interpreted in clinical context. Symptoms, history, medications, kidney function, and other lab results all affect the meaning of the calculation. A normal value does not exclude disease, and an elevated value does not prove one specific diagnosis.
If used appropriately, the calculator is a helpful clue. When used by itself, it can be misleading. That is why it should always inform broader medical evaluation rather than replace it.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the gap from serum electrolytes and help assess metabolic acidosis. It acts as a screening tool for an acid-base disorder and can point toward a high-gap or normal-gap pattern. Clinicians use it to guide clinical interpretation and guide the next diagnostic steps.
How do you calculate the anion gap in metabolic acidosis?
The usual formula is sodium - (chloride + bicarbonate). Some versions also include potassium. The calculation uses values from the serum chemistry panel and produces a calculated value that is compared with the lab’s reference range.
What does a high anion gap mean?
A high gap usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion. It suggests a high anion gap metabolic acidosis and usually warrants a focused diagnostic workup.
Why do you correct the anion gap for albumin?
You correct it because albumin strongly affects the measured gap. With hypoalbuminemia, the uncorrected result may look normal even when a true metabolic acid load is present. The corrected anion gap gives a more accurate picture of acid-base balance and helps avoid missed diagnoses.
What conditions cause a normal anion gap metabolic acidosis?
Typical causes are intestinal fluid loss, renal tubular acidosis, and other conditions leading to bicarbonate loss with a compensatory rise in chloride, also known as hyperchloremic acidosis. While the gap is normal, the patient still has a real metabolic acidosis that needs evaluation.